
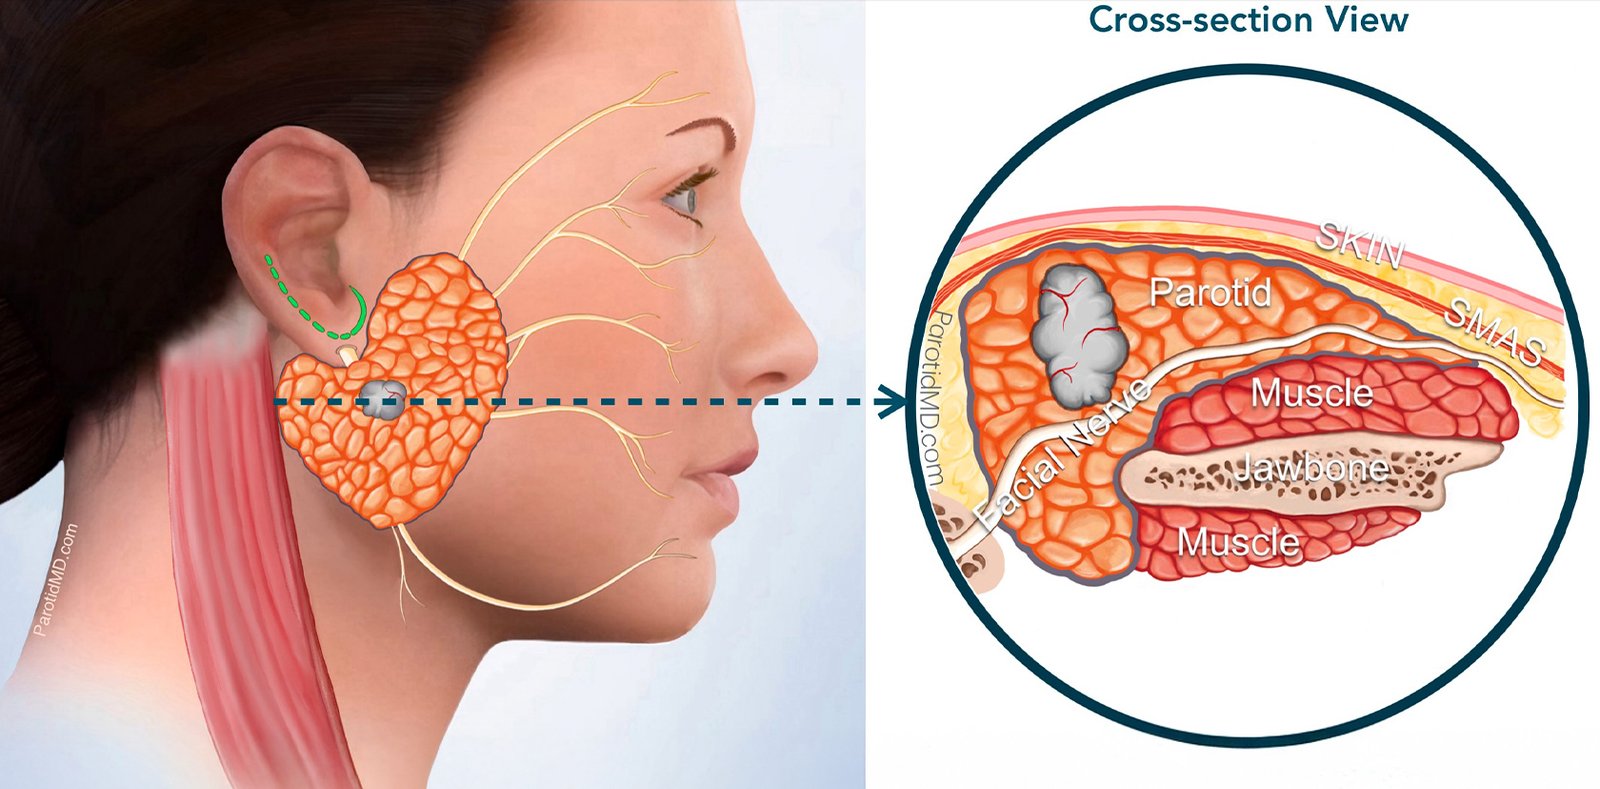
Navigating the complexities of head and neck tumors requires a deep understanding of both the disease process and the intricate anatomy of the affected regions. For many patients, the initial symptoms may seem innocuous—a persistent sore throat, a mouth ulcer that refuses to heal, or a subtle change in voice. However, early detection and prompt intervention by a dedicated head and neck specialist can dramatically alter the course of the disease. The philosophy of modern surgical oncology dictates that removing the cancer is only half the battle; restoring the patient's form and function is equally imperative. This dual objective has given rise to the specialized field of microvascular reconstructive surgery, which works hand-in-hand with tumor resection. As we delve into the specifics of treatment, it becomes evident that a multidisciplinary approach, combining the skills of surgeons, radiation oncologists, and medical oncologists, provides the most robust defense against these aggressive malignancies.
Understanding the Anatomy and Pathology
The oral cavity and the broader head and neck region consist of multiple sub-sites, each with its own unique biological behavior and lymphatic drainage patterns. The oral cavity includes the lips, the anterior two-thirds of the tongue, the buccal mucosa (inner lining of the cheeks), the floor of the mouth, the hard palate, and the upper and lower gums (alveolus). Tumors arising in different sub-sites present unique surgical challenges. For instance, a tumor on the lateral border of the tongue may spread quickly to the lymph nodes in the neck due to the tongue's rich lymphatic network. In contrast, a tumor on the hard palate might invade the maxillary sinus or nasal cavity, requiring a completely different surgical approach. Most oral cancers are squamous cell carcinomas, originating from the flat cells that line the mouth and throat. Understanding the histopathology of the tumor—its grade, depth of invasion, and perineural spread—is crucial for the surgical oncologist to plan the extent of resection and determine the necessity of postoperative radiation or chemotherapy.
Primary Risk Factors and Causes
The etiology of oral and head and neck cancers is heavily influenced by lifestyle and environmental factors. In India and Southeast Asia, the predominant cause of oral cancer is the pervasive use of smokeless tobacco, betel quid (paan), areca nut (supari), and gutkha. These substances contain potent carcinogens that continuously irritate the mucosal lining of the mouth, leading to premalignant lesions such as leukoplakia (white patches), erythroplakia (red patches), and oral submucous fibrosis (OSMF). OSMF is particularly insidious, causing severe restriction in mouth opening and a high rate of malignant transformation. Smoking cigarettes, bidis, and cigars exponentially increases the risk, especially when combined with heavy alcohol consumption. The synergistic effect of alcohol and tobacco is well-documented, multiplying the carcinogenic impact on the tissues of the throat and mouth. In recent years, there has also been a significant rise in head and neck cancers associated with the Human Papillomavirus (HPV), particularly affecting the oropharynx (tonsils and base of tongue). HPV-related cancers often present in younger, non-smoking individuals and generally have a better prognosis and response to treatment compared to tobacco-induced cancers.
The Path to an Accurate Diagnosis
Recognizing the early symptoms of head and neck cancer can mean the difference between a minor surgical procedure and a massive, life-altering operation. Patients should be vigilant about any unexplained numbness in the facial or oral regions, loosening of teeth without apparent dental disease, or a persistent earache that does not respond to standard treatments (which can often be referred pain from a tumor in the throat). The diagnostic journey typically begins with a thorough clinical examination, including a fiber-optic endoscopy to visualize the hidden areas of the throat and larynx. Following this, a targeted biopsy is performed. For neck masses, a Fine Needle Aspiration Cytology (FNAC) is a quick and relatively painless way to obtain cells for analysis. Radiographic evaluation is indispensable for surgical planning. High-resolution MRI is particularly useful for assessing soft tissue involvement and perineural spread (cancer tracking along nerves), while a CT scan is excellent for evaluating bone erosion, such as tumor invasion into the mandible (lower jaw) or maxilla (upper jaw).
Advanced Oncologic Surgery Techniques
Modern head and neck surgery has evolved to maximize tumor eradication while minimizing collateral damage to the patient. For tumors located in the deeper regions of the throat, such as the oropharynx or larynx, traditional open surgeries often required splitting the jaw or making large neck incisions. Today, selected cases can be treated using Transoral Robotic Surgery (TORS) or Transoral Laser Microsurgery (TLM). These minimally invasive techniques allow the surgeon to access and remove tumors through the mouth using high-definition 3D cameras and articulating robotic arms, leading to dramatically reduced recovery times, less scarring, and better preservation of swallowing and speech functions. However, for large, invasive tumors of the oral cavity and facial bones, open surgery remains the gold standard. In these complex cases, the surgical oncologist employs a 3D virtual surgical planning system, using computer models of the patient's anatomy to precisely map out the bone cuts and the reconstructive plan before the patient even enters the operating room.
Restoring Form and Function
The integration of microvascular reconstructive surgery with oncologic resection is what defines a world-class head and neck cancer center. The reconstructive process is tailored entirely to the specific defect created by the tumor removal. If a massive portion of the tongue is resected (total or subtotal glossectomy), an Anterolateral Thigh (ALT) flap or a Radial Forearm Free Flap (RAFF) is used to create a new, bulky neo-tongue, enabling the patient to swallow and articulate speech. When the upper jaw (maxilla) or lower jaw (mandible) is removed, vascularized bone flaps (like the fibula or scapula) are sculpted to perfectly match the patient's native facial contours, often guided by custom-made 3D-printed cutting guides and titanium plates. The success of these microvascular procedures approaches 95-98% in expert hands. The profound impact of reconstruction goes beyond physical restoration; it provides immense psychological support, allowing patients to confidently reintegrate into society and maintain a high quality of life after surviving cancer.
Postoperative Care and the Road to Normalcy
Recovery from major head and neck surgery, particularly when combined with microvascular reconstruction, is a gradual process that requires a dedicated, multidisciplinary team approach. Patients typically spend the first few days in the Intensive Care Unit (ICU) for close monitoring of the reconstructed flap and airway management. Nutritional support is paramount; since patients cannot eat by mouth initially, feeding is facilitated through a nasogastric or PEG tube. As healing progresses, intensive speech and swallow therapy commence. The brain and muscles must adapt to the newly reconstructed anatomy. Physical therapy is also crucial for the recovery of the donor site (where the tissue was harvested). Consistent follow-up and adherence to rehabilitation protocols determine the ultimate functional success of the surgery. Dr. Manish S. Tiwari and his dedicated oncology team in Kolkata are committed to providing unparalleled surgical excellence and compassionate postoperative care. By combining aggressive tumor resection with state-of-the-art microvascular reconstruction, they ensure that every patient is given the best possible chance at a cancer-free life with dignity and optimal functional restoration.