
A diagnosis of oral or head and neck cancer is a life-altering event that brings forth a multitude of questions and concerns. The journey from diagnosis to recovery is paved with critical decisions, the most important being the selection of an experienced surgical oncologist. The head and neck region is arguably the most complex area of the human body, housing the vital apparatus for breathing, eating, speaking, and expressing emotion. Consequently, surgical intervention in this area requires an unparalleled level of precision and expertise. Today, the field of head and neck oncology has evolved far beyond mere tumor removal. It encompasses a holistic approach where oncologic safety is seamlessly integrated with functional rehabilitation and aesthetic preservation. Advanced imaging, multidisciplinary tumor boards, and state-of-the-art reconstructive techniques have transformed the prognosis for many patients. Understanding the nuances of the disease and the available treatment modalities empowers patients to take an active role in their healthcare journey, leading to better psychological and physical outcomes.
Understanding the Anatomy and Pathology
The oral cavity and the broader head and neck region consist of multiple sub-sites, each with its own unique biological behavior and lymphatic drainage patterns. The oral cavity includes the lips, the anterior two-thirds of the tongue, the buccal mucosa (inner lining of the cheeks), the floor of the mouth, the hard palate, and the upper and lower gums (alveolus). Tumors arising in different sub-sites present unique surgical challenges. For instance, a tumor on the lateral border of the tongue may spread quickly to the lymph nodes in the neck due to the tongue's rich lymphatic network. In contrast, a tumor on the hard palate might invade the maxillary sinus or nasal cavity, requiring a completely different surgical approach. Most oral cancers are squamous cell carcinomas, originating from the flat cells that line the mouth and throat. Understanding the histopathology of the tumor—its grade, depth of invasion, and perineural spread—is crucial for the surgical oncologist to plan the extent of resection and determine the necessity of postoperative radiation or chemotherapy.
Primary Risk Factors and Causes
The etiology of oral and head and neck cancers is heavily influenced by lifestyle and environmental factors. In India and Southeast Asia, the predominant cause of oral cancer is the pervasive use of smokeless tobacco, betel quid (paan), areca nut (supari), and gutkha. These substances contain potent carcinogens that continuously irritate the mucosal lining of the mouth, leading to premalignant lesions such as leukoplakia (white patches), erythroplakia (red patches), and oral submucous fibrosis (OSMF). OSMF is particularly insidious, causing severe restriction in mouth opening and a high rate of malignant transformation. Smoking cigarettes, bidis, and cigars exponentially increases the risk, especially when combined with heavy alcohol consumption. The synergistic effect of alcohol and tobacco is well-documented, multiplying the carcinogenic impact on the tissues of the throat and mouth. In recent years, there has also been a significant rise in head and neck cancers associated with the Human Papillomavirus (HPV), particularly affecting the oropharynx (tonsils and base of tongue). HPV-related cancers often present in younger, non-smoking individuals and generally have a better prognosis and response to treatment compared to tobacco-induced cancers.
Warning Signs and Diagnostic Modalities
Early detection remains the single most important factor in achieving a cure in head and neck oncology. Unfortunately, many patients ignore the initial warning signs, attributing them to benign conditions. Key symptoms that warrant immediate evaluation by a specialist include a persistent mouth ulcer that fails to heal within two to three weeks, unexplained bleeding in the mouth, difficulty or pain during swallowing (dysphagia), a change in voice or persistent hoarseness, and the sudden appearance of a painless lump in the neck. To accurately diagnose and stage the disease, a multifaceted approach is required. The gold standard for diagnosis is a biopsy, where a small tissue sample is extracted and examined under a microscope. Once malignancy is confirmed, advanced imaging techniques come into play. Contrast-enhanced CT scans or MRI scans provide detailed cross-sectional views of the tumor, delineating its exact size, depth of tissue invasion, and involvement of adjacent bones or blood vessels. A PET-CT scan may also be ordered to detect microscopic spread to regional lymph nodes or distant organs, ensuring that the treatment plan addresses the entirety of the disease.
Surgical Interventions and Treatment Strategies
The cornerstone of curative treatment for early and moderately advanced oral cancers is surgical resection. The primary objective is to achieve 'negative margins'—removing the tumor entirely along with a surrounding cuff of healthy tissue to ensure no microscopic cancer cells are left behind. Depending on the tumor's location, procedures can range from a simple wide local excision of a tongue lesion (partial glossectomy) to a massive composite resection that includes the removal of a portion of the jawbone (mandibulectomy or maxillectomy). Because oral cancers frequently metastasize to the lymph nodes in the neck, a 'neck dissection' is concurrently performed. This meticulous procedure involves carefully stripping the fat and lymph nodes from the vital nerves and blood vessels of the neck. For advanced cases, surgery is often just the first step in a multimodal treatment plan. Based on the final pathology report, the patient may require adjuvant (post-operative) radiation therapy or concurrent chemo-radiation to eradicate any lingering microscopic disease and significantly reduce the risk of recurrence.
The Miracle of Microvascular Reconstruction
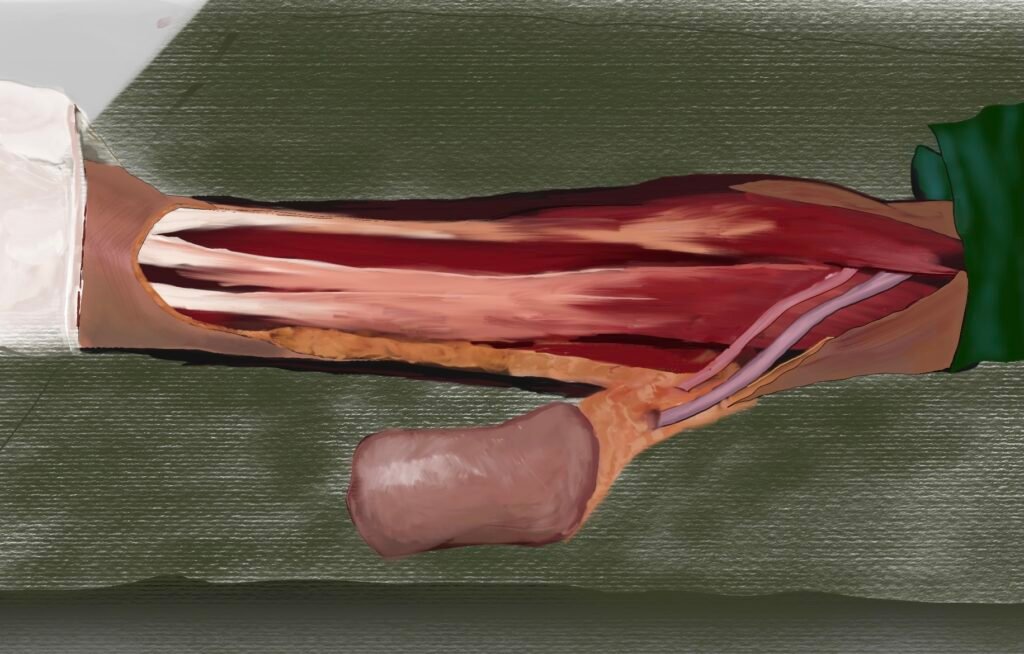
Removing a large tumor from the head or neck inevitably creates a significant structural and functional deficit. Decades ago, patients were left with severe disfigurements and lifelong disabilities in eating and speaking. Today, the advent of microvascular free flap reconstructive surgery has revolutionized patient rehabilitation. This highly intricate procedure involves harvesting living tissue—skin, muscle, and bone—from a 'donor site' on the patient's own body, such as the forearm, thigh, or lower leg (fibula). The surgeon transplants this tissue to the head and neck to rebuild the missing structures. Using a high-powered operating microscope and sutures finer than a human hair, the surgeon meticulously connects the tiny arteries and veins of the transplanted tissue to the blood vessels in the neck. This restores blood flow and keeps the reconstructed tissue alive. For example, a fibula free flap can be used to completely rebuild a resected jawbone, allowing for the eventual placement of dental implants and a return to normal chewing function.
Long-Term Rehabilitation and Follow-Up
Surviving head and neck cancer is a monumental victory, but the journey continues well after the surgical incisions have healed. Comprehensive postoperative rehabilitation is vital for maximizing the functional outcomes of reconstructive surgery. Patients engage in rigorous swallowing exercises to prevent aspiration and speech therapy to improve articulation. Dietary modifications are gradually introduced as the patient transitions from tube feeding back to an oral diet. The psychological impact of facial surgery cannot be overstated, and access to counseling and support groups forms a critical component of holistic cancer care. Furthermore, rigorous surveillance is mandatory for the first five years post-treatment to monitor for any signs of recurrence. Regular clinical examinations and imaging scans provide peace of mind and ensure any issues are addressed immediately. If you or a loved one are facing a diagnosis of oral or head and neck cancer, choosing an expert who manages both the oncologic and reconstructive aspects of care is essential. Dr. Manish Tiwari represents the pinnacle of surgical expertise in Kolkata, offering hope, cutting-edge treatment, and comprehensive rehabilitation to his patients.