
When faced with a diagnosis of cancer in the head, neck, or oral cavity, the sheer volume of information can be overwhelming. The anatomical complexity of the mouth, throat, and neck requires a highly specialized approach to treatment. Unlike other forms of cancer where surgery might be straightforward, head and neck oncology demands a delicate balance between aggressively eradicating the tumor and preserving the vital functions of speech, swallowing, and appearance. Selecting the right specialist is not just a choice; it is the most critical decision a patient and their family will make. A specialized surgical oncologist brings years of targeted experience, understanding the intricate web of nerves, blood vessels, and muscles that define the human face and neck. With the rapid advancement of modern medical technology, the paradigms of treatment have shifted significantly towards minimally invasive techniques and immediate reconstruction. Patients today have access to world-class care that prioritizes both survival and the quality of life post-treatment.
The Complex Structures of the Head and Neck
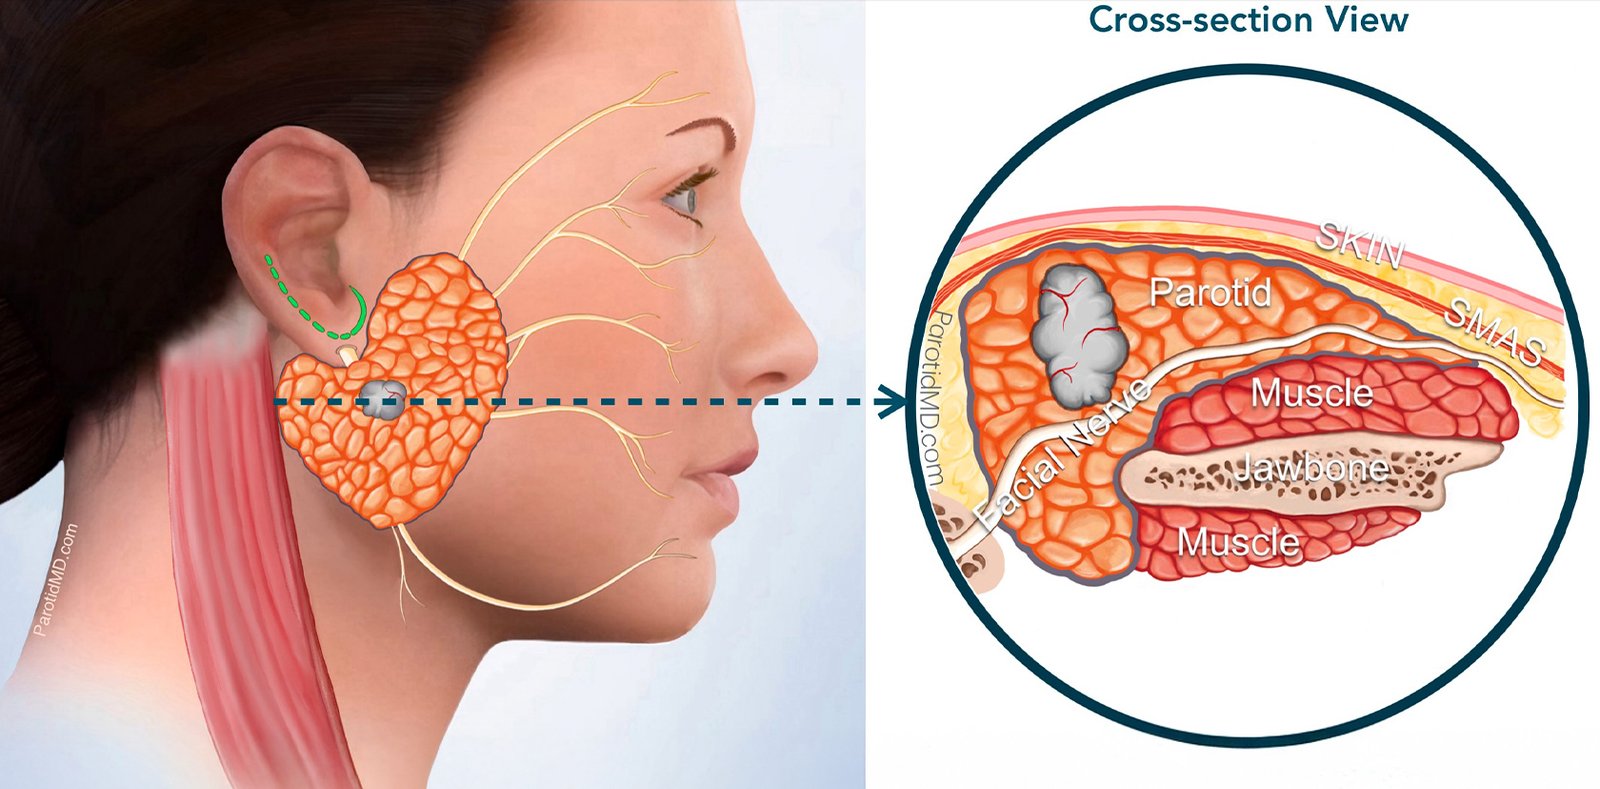
To fully appreciate the intricacies of head and neck surgery, one must understand the dense concentration of vital structures in this relatively small anatomical area. The neck houses major blood vessels, including the carotid arteries and jugular veins, which supply and drain the brain. It also contains critical nerves, such as the vagus nerve, the hypoglossal nerve (controlling tongue movement), and the facial nerve. When a tumor develops in the parotid gland, for example, it often wraps around the facial nerve, making its surgical removal an exercise in extreme precision to avoid facial paralysis. Furthermore, the lymphatic system in the neck, consisting of hundreds of lymph nodes divided into different levels, acts as the primary pathway for the metastatic spread of head and neck cancers. A comprehensive surgical plan almost always includes a neck dissection—the systematic removal of these lymph nodes—to stage the disease accurately and prevent regional recurrence.
Understanding the Etiology of the Disease
While tobacco and alcohol remain the most significant culprits in the development of head and neck malignancies, several other risk factors contribute to the disease burden. Poor oral hygiene and chronic dental trauma, such as ill-fitting dentures or sharp, jagged teeth that constantly rub against the tongue or cheek lining, can induce chronic inflammation. Over time, this constant cellular irritation can trigger mutations that lead to cancer. Nutritional deficiencies, particularly a lack of fresh fruits and vegetables rich in antioxidants, can weaken the body's natural defense mechanisms against cellular damage. Occupational exposures to certain dusts and chemicals, such as wood dust, nickel dust, and formaldehyde, are known risk factors for cancers of the paranasal sinuses and nasal cavity. Additionally, genetic predispositions and inherited syndromes, though rare, can increase an individual's susceptibility. Understanding these risk factors is not only crucial for prevention but also helps the surgical oncologist tailor the screening and diagnostic process for high-risk individuals.
Warning Signs and Diagnostic Modalities
Early detection remains the single most important factor in achieving a cure in head and neck oncology. Unfortunately, many patients ignore the initial warning signs, attributing them to benign conditions. Key symptoms that warrant immediate evaluation by a specialist include a persistent mouth ulcer that fails to heal within two to three weeks, unexplained bleeding in the mouth, difficulty or pain during swallowing (dysphagia), a change in voice or persistent hoarseness, and the sudden appearance of a painless lump in the neck. To accurately diagnose and stage the disease, a multifaceted approach is required. The gold standard for diagnosis is a biopsy, where a small tissue sample is extracted and examined under a microscope. Once malignancy is confirmed, advanced imaging techniques come into play. Contrast-enhanced CT scans or MRI scans provide detailed cross-sectional views of the tumor, delineating its exact size, depth of tissue invasion, and involvement of adjacent bones or blood vessels. A PET-CT scan may also be ordered to detect microscopic spread to regional lymph nodes or distant organs, ensuring that the treatment plan addresses the entirety of the disease.
Surgical Interventions and Treatment Strategies
The cornerstone of curative treatment for early and moderately advanced oral cancers is surgical resection. The primary objective is to achieve 'negative margins'—removing the tumor entirely along with a surrounding cuff of healthy tissue to ensure no microscopic cancer cells are left behind. Depending on the tumor's location, procedures can range from a simple wide local excision of a tongue lesion (partial glossectomy) to a massive composite resection that includes the removal of a portion of the jawbone (mandibulectomy or maxillectomy). Because oral cancers frequently metastasize to the lymph nodes in the neck, a 'neck dissection' is concurrently performed. This meticulous procedure involves carefully stripping the fat and lymph nodes from the vital nerves and blood vessels of the neck. For advanced cases, surgery is often just the first step in a multimodal treatment plan. Based on the final pathology report, the patient may require adjuvant (post-operative) radiation therapy or concurrent chemo-radiation to eradicate any lingering microscopic disease and significantly reduce the risk of recurrence.
Restoring Form and Function
The integration of microvascular reconstructive surgery with oncologic resection is what defines a world-class head and neck cancer center. The reconstructive process is tailored entirely to the specific defect created by the tumor removal. If a massive portion of the tongue is resected (total or subtotal glossectomy), an Anterolateral Thigh (ALT) flap or a Radial Forearm Free Flap (RAFF) is used to create a new, bulky neo-tongue, enabling the patient to swallow and articulate speech. When the upper jaw (maxilla) or lower jaw (mandible) is removed, vascularized bone flaps (like the fibula or scapula) are sculpted to perfectly match the patient's native facial contours, often guided by custom-made 3D-printed cutting guides and titanium plates. The success of these microvascular procedures approaches 95-98% in expert hands. The profound impact of reconstruction goes beyond physical restoration; it provides immense psychological support, allowing patients to confidently reintegrate into society and maintain a high quality of life after surviving cancer.
Postoperative Care and the Road to Normalcy
Recovery from major head and neck surgery, particularly when combined with microvascular reconstruction, is a gradual process that requires a dedicated, multidisciplinary team approach. Patients typically spend the first few days in the Intensive Care Unit (ICU) for close monitoring of the reconstructed flap and airway management. Nutritional support is paramount; since patients cannot eat by mouth initially, feeding is facilitated through a nasogastric or PEG tube. As healing progresses, intensive speech and swallow therapy commence. The brain and muscles must adapt to the newly reconstructed anatomy. Physical therapy is also crucial for the recovery of the donor site (where the tissue was harvested). Consistent follow-up and adherence to rehabilitation protocols determine the ultimate functional success of the surgery. Dr. Manish S. Tiwari and his dedicated oncology team in Kolkata are committed to providing unparalleled surgical excellence and compassionate postoperative care. By combining aggressive tumor resection with state-of-the-art microvascular reconstruction, they ensure that every patient is given the best possible chance at a cancer-free life with dignity and optimal functional restoration.